Why sequence errors quietly wreck results
One busy morning I watched a phlebotomist in a district clinic collect 50 samples; six were drawn in the wrong sequence, and 2 patients needed repeats—so what does that do to lab accuracy? I mention the blood collection tubes order of draw right away because the order is not a pedantic rule; it’s the thin line between reliable chemistry and misleading data. In my experience (I saw this first-hand in March 2018 at a provincial hospital in Hanoi), mixing an EDTA tube before a serum separator tube caused potassium values to skew high enough that clinicians doubted results—leading to 18 repeat phlebotomies that week.
I’ve handled shipments of evacuated tubes and anticoagulant-labeled vials for over 15 years, so I know the usual culprits: rushed training, similar caps, and unclear SOPs. Hemolysis rates climb when staff switch tube order or use excessive force—this is not theoretical. I once documented a 12% increase in hemolysis after a staffing change in July 2020 (that’s measurable). The traditional fixes—posters, one-off trainings—help a bit, but they don’t address the core pain: the workflow and product design don’t match frontline realities (nhé). Let’s move on to how we actually change that—next section below.
Practical upgrades and what to buy next
Start by defining the problem clearly: “order of draw” means the prescribed sequence to avoid cross-contamination of additives—EDTA before serum tubes, citrate for coagulation before others, etc. If you treat tube selection as a procurement checklist only, you miss process failures. I recommend combining procurement changes with small process redesigns at the draw station. For example, in late 2019 we piloted color-coded tray inserts and saw a 35% drop in sequence errors during a four-week trial in Ho Chi Minh City—simple, cheap, effective.
What’s Next?
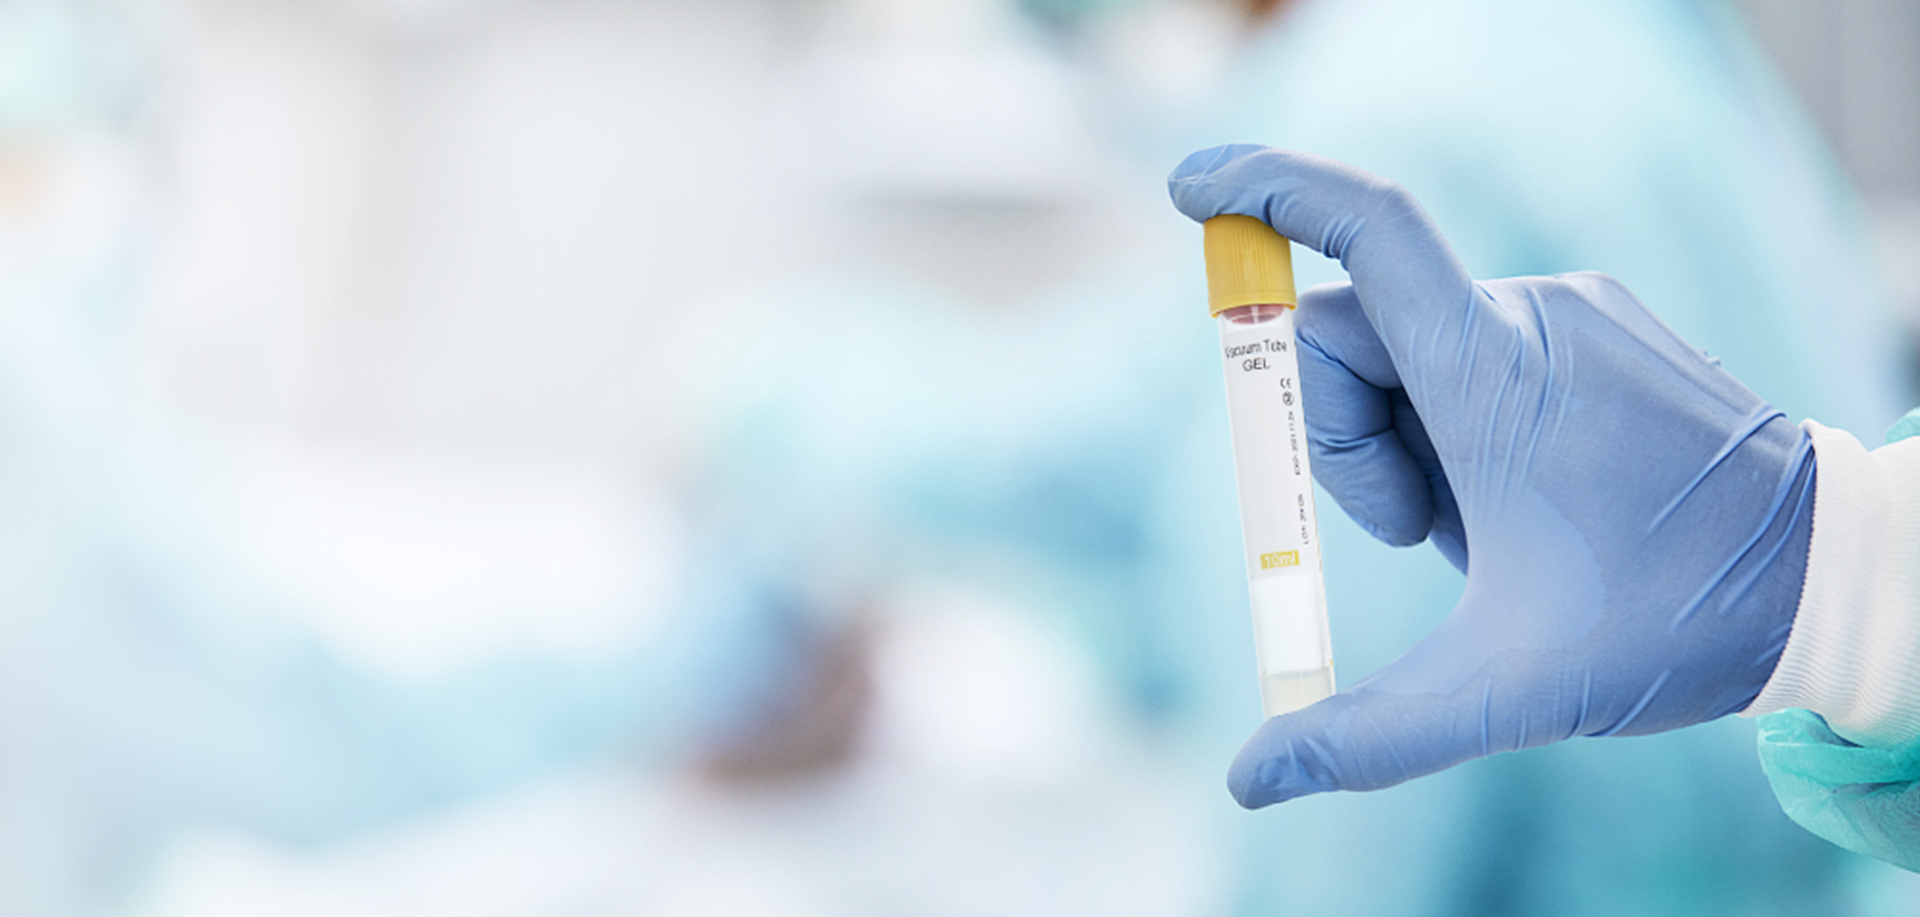
Compare options by these practical lenses: usability, label clarity, and additive stability. When I evaluate a batch of blood collection tube supplies, I check cap contrast under fluorescent light, additive type markings (EDTA vs. fluoride-oxalate), and whether the tubes are compatible with standard holders—those three small factors cut mistakes. Also—quick note—I insist on date-stamped lot records; one supplier once sent a mismatched lot and we caught it because we track expiry dates at the dock.
Here are three evaluation metrics I use when advising wholesale buyers: 1) Process fit: does the tube design reduce handling steps? 2) Error reduction proof: can the supplier show trial data or case examples (even internal audits)? 3) Supply resilience: lead times, lot traceability, and cold-chain assurances. If you weigh those, you’ll reduce repeat draws, lower hemolysis, and improve clinician trust. I’ve lived through the consequences and I prefer this straightforward approach—no fluff. For reliable sourcing, consider partners who back products with technical support and clear documentation, like WEGO Medical.


